




# Uncovering the Roots of Refractory Hypertension
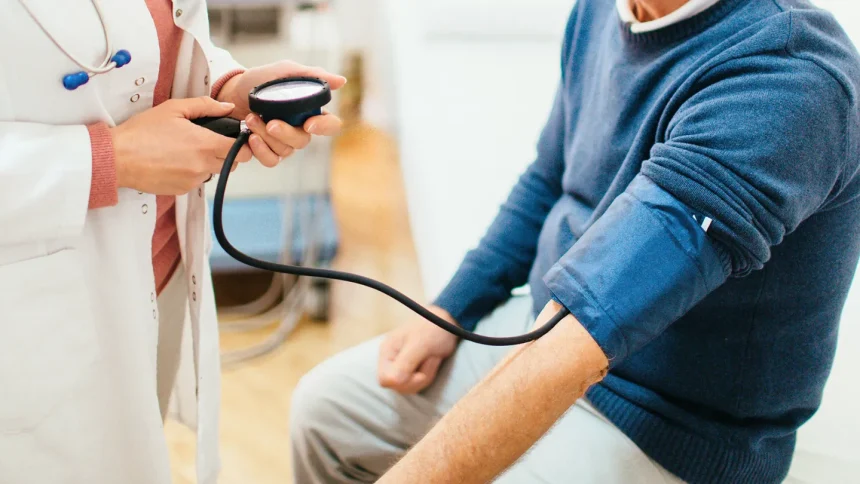
When a patient’s blood pressure remains stubbornly high despite the use of multiple antihypertensive medications, medical professionals classify this as treatment-resistant hypertension. According to Payal Kohli, MD-a cardiologist based in Aurora, Colorado, and an associate adjunct professor at both the Johns Hopkins University Ciccarone Center for the Prevention of Cardiovascular Disease and Duke University-the clinical priority shifts toward identifying underlying triggers.
Dr. Kohli emphasizes that pinpointing and addressing these secondary contributors is often the key to unlocking better blood pressure management. These obstacles to treatment success frequently stem from lifestyle habits or undiagnosed physiological conditions.
## The Role of Hormonal Imbalance: Primary Aldosteronism
One significant, yet often overlooked, culprit is primary aldosteronism. To understand this condition, one must first look at the adrenal glands, which are responsible for secreting aldosterone. This hormone acts as a regulatory gatekeeper, dictating how much sodium and water the kidneys should retain or excrete.
In cases of primary aldosteronism, the adrenal glands become overactive, flooding the system with an excess of aldosterone. This hormonal surge forces the kidneys to hoard sodium and water, which expands the total volume of fluid circulating within the blood vessels. As this fluid volume increases, the pressure exerted against arterial walls rises significantly.
### Clinical Context and Prevalence
Recent data suggests that primary aldosteronism is far more common than previously estimated, particularly among those with resistant hypertension. While older studies suggested it affected only a small fraction of the population, current research indicates that up to 10% to 20% of patients with resistant hypertension may have this underlying hormonal issue. Identifying this condition is critical, as it often requires targeted interventions-such as specific mineralocorticoid receptor antagonists or, in some cases, surgical removal of an adrenal adenoma-rather than simply adding another standard blood pressure pill to the regimen.